
⚕️ Educational content only. This article is intended for biomedical science students and those interested in laboratory medicine. It is not medical advice. Consult a healthcare professional for personal health concerns.
Vitamin B12 (cobalamin) and folate (vitamin B9) are essential water-soluble vitamins required for DNA synthesis, red blood cell production, and neurological function. Both are measured via routine blood tests and deficiency in either can lead to megaloblastic anaemia. Understanding the biochemistry and laboratory approach helps interpret results accurately.
Key Takeaways
- Both B12 and folate are required for thymidine synthesis; deficiency impairs DNA replication and causes megaloblastic anaemia.
- B12 deficiency also causes subacute combined degeneration of the spinal cord; folate deficiency does not.
- Serum B12 levels can be normal in functional B12 deficiency; methylmalonic acid (MMA) and homocysteine are more sensitive markers.
- Folate deficiency is commonly dietary; B12 deficiency is often due to malabsorption (pernicious anaemia, gastrectomy, ileal disease).
Why B12 and Folate Matter
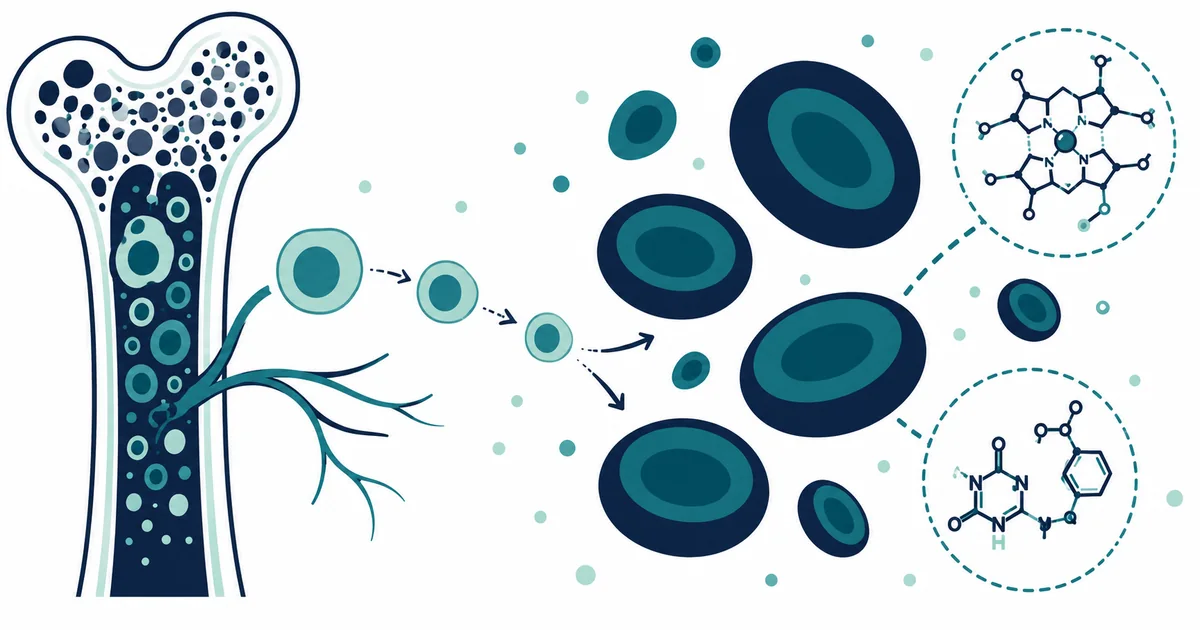
Both vitamins are co-factors in one-carbon metabolism. Folate (as 5,10-methylenetetrahydrofolate) is required for thymidylate synthesis. B12 is needed to regenerate tetrahydrofolate from 5-methyltetrahydrofolate. When either is deficient, DNA synthesis is impaired, and cells unable to divide properly — particularly rapidly dividing cells like erythroblasts — become enlarged. This produces macrocytic, megaloblastic red cells and hypersegmented neutrophils on the blood film.
Causes of Deficiency
Vitamin B12 Deficiency
The commonest cause in developed countries is pernicious anaemia — an autoimmune condition where antibodies target gastric parietal cells or intrinsic factor (IF), preventing B12 absorption in the terminal ileum. Other causes include: gastrectomy or gastric bypass (loss of parietal cells), ileal resection or Crohn’s disease (loss of absorption site), strict veganism (B12 is found only in animal products), metformin use (reduces B12 absorption), and bacterial overgrowth (competing for B12).
Folate Deficiency
Folate deficiency is most commonly dietary (poor intake of green vegetables, legumes, and fortified foods). It is also seen in: pregnancy and haemolytic anaemia (increased demand), malabsorption (coeliac disease, Crohn’s), alcohol excess (impairs absorption and increases excretion), and drugs such as methotrexate, trimethoprim, and phenytoin (folate antagonists).
Laboratory Tests
Serum B12: The first-line test. Normal range is approximately 150–700 pmol/L (varies by lab). Low levels suggest deficiency, but borderline results are common. Serum B12 can be normal in functional B12 deficiency, particularly in patients with high serum haptocorrin. Red cell folate reflects longer-term folate status (2–3 months) compared to serum folate (recent intake). Methylmalonic acid (MMA) is elevated specifically in B12 deficiency (it accumulates when the B12-dependent enzyme methylmalonyl-CoA mutase cannot function). Homocysteine is elevated in both B12 and folate deficiency. These metabolite tests are useful when B12/folate results are borderline or clinically inconsistent.
Blood Film Findings
Megaloblastic anaemia produces macrocytic red cells (MCV >100 fL), oval macrocytes, and hypersegmented neutrophils (≥5 lobes in >5% of neutrophils). These findings indicate impaired DNA synthesis regardless of the underlying cause. Combined with low B12 or folate, they confirm megaloblastic anaemia. A bone marrow examination may show megaloblastic change in the erythroid lineage if further evaluation is needed.
The Importance of Testing Both
Treating folate deficiency with folic acid supplementation when undiagnosed B12 deficiency coexists can correct the anaemia but unmask or worsen the neurological complications of B12 deficiency. Therefore, B12 levels should always be checked before starting folate replacement in patients with megaloblastic anaemia.
References
- NHS. Vitamin B12 or folate deficiency anaemia. nhs.uk
- NIH Office of Dietary Supplements. Vitamin B12 Fact Sheet. ods.od.nih.gov
- Stabler SP. Vitamin B12 deficiency. N Engl J Med. 2013;368(2):149-160.
More questions answered
What does the vitamin B12 and folate tests actually measure?
The vitamin B12 and folate tests measures the concentrations of vitamin B12 and folate-related markers in blood. The test is usually performed on serum or plasma, although the exact sample and method depend on the laboratory. The result is often interpreted alongside full blood count, blood film and selected metabolic markers because one measurement rarely answers every clinical question. The practical takeaway is to read the value in the context of the laboratory report rather than treating it as a stand-alone diagnosis.
Do I need to fast before the vitamin B12 and folate tests?
Fasting is not automatically required just because this test has been requested. Preparation depends on the exact test request, so the laboratory or healthcare service should provide any fasting or timing instructions. If other tests are ordered at the same time, their preparation requirements may determine how the blood sample should be collected. The safest approach is to follow the collection instructions given for the specific appointment rather than fasting unnecessarily.
What can affect the vitamin B12 and folate tests result besides disease?
A vitamin B12 and folate tests result can be influenced by diet, absorption, medicines, supplements and assay limitations. Some effects happen before analysis, which laboratories describe as pre-analytical factors, while others reflect genuine biological variation. The laboratory may also consider sample quality and analytical limitations before releasing a result. This is why an unexpected value may need context or repeat testing rather than an immediate conclusion.
Why might the vitamin B12 and folate tests be repeated?
A repeat test can help show whether a result is persistent, changing or likely to have been affected by a temporary factor. Comparing results over time creates a trend, which can be more informative than one isolated measurement. Repetition may also be needed when the sample was unsuitable or when the first result requires confirmation according to laboratory procedure. A healthcare professional decides whether repeat testing is clinically useful.
Why can the reference range for the vitamin B12 and folate tests differ between laboratories?
Laboratories may use different reference intervals because their analysers, reagents, calibration systems and reference populations are not always identical. Even when two laboratories measure the same analyte, differences in assay methods can produce different reporting ranges or units. The correct comparison is therefore the range printed on the same laboratory report as the result. A range found online should not replace the laboratory’s own interval.
How is the vitamin B12 and folate tests measured in the laboratory?
The sample is first checked to make sure it is suitable for testing, then the serum or plasma is processed according to the laboratory method. Measurement is typically performed using validated immunoassays or related laboratory methods, with quality-control material used to check that the analytical system is behaving as expected. Results that trigger laboratory rules may be reviewed, repeated or investigated before release. This controlled quality process helps reduce avoidable analytical errors.
Can the vitamin B12 and folate tests diagnose a condition by itself?
No single vitamin B12 and folate tests result should usually be treated as a complete diagnosis on its own. The test can support investigation of deficiency and macrocytic blood-count patterns, but the meaning depends on clinical context, other laboratory findings and sometimes imaging or examination. An abnormal value can have more than one explanation, while a value inside the reference interval does not exclude every condition. Personal interpretation should therefore be discussed with a healthcare professional.